

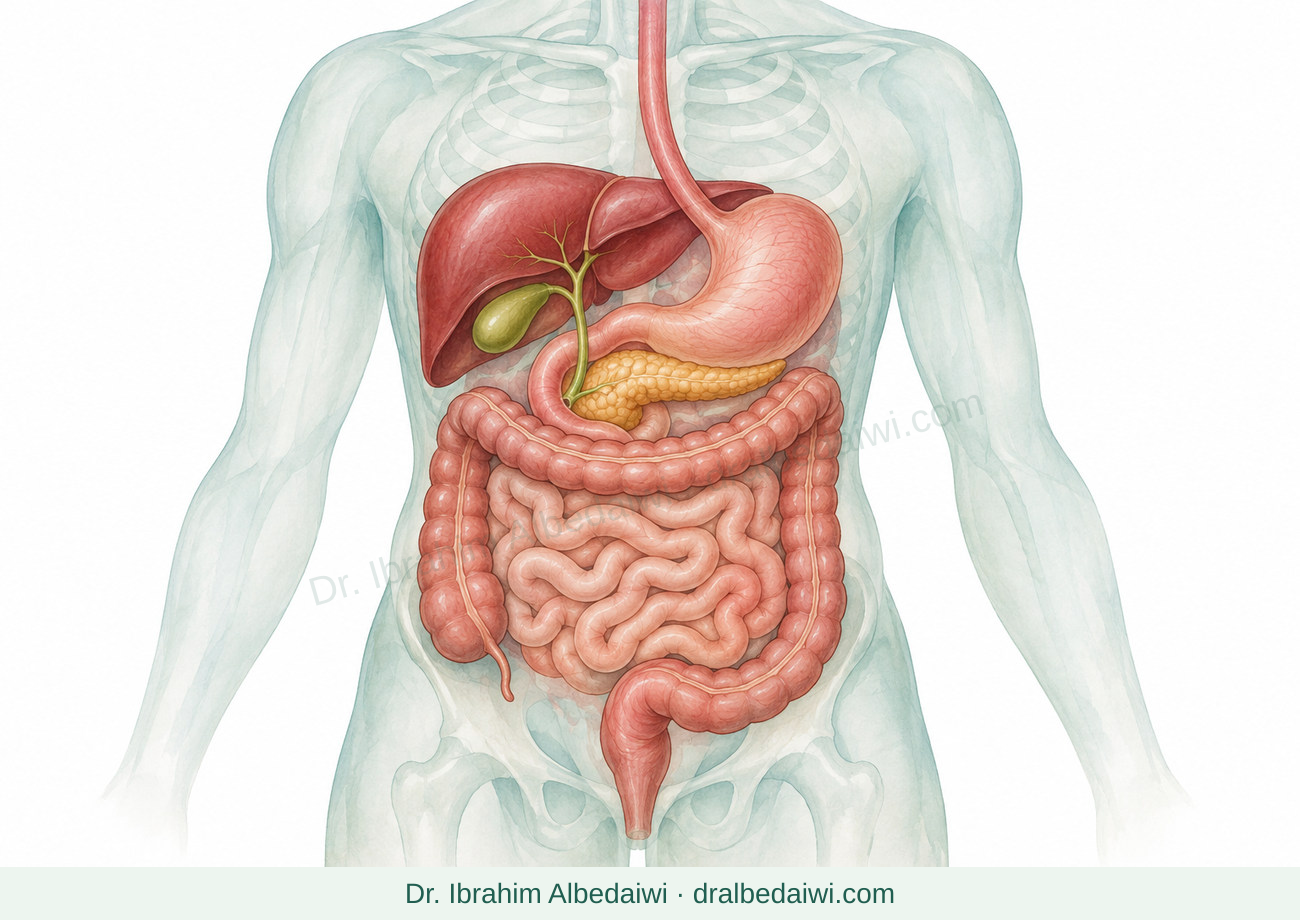

Liver cirrhosis (F4)
Content date: 14 November 2026
Treating the cause and monitoring complications can help keep the liver stable. Good nutrition and knowing warning signs are essential parts of care.
Your next step
Review prescribed medicines for ascites or confusion and the date of your next liver scan.
Get urgent help: Vomiting blood or black stools, new confusion or drowsiness, fever or abdominal pain with ascites, markedly reduced urine, or breathlessness.
How does cirrhosis differ from earlier fibrosis?
- Persistent liver injury can produce scar tissue, called fibrosis. In the F0–F4 staging system, F1–F3 are fibrosis before cirrhosis; F3 is already advanced fibrosis. F4 is cirrhosis: scarring alters the liver’s structure and may affect blood flow and liver function.
- It can result from viruses, steatohepatitis, autoimmune conditions or bile duct diseases. Treating the cause may improve health and reduce complications; the diagnosis alone does not mean a transplant is immediately needed.
Why do symptoms differ between people?
- In compensated cirrhosis, the liver is still coping and these major complications have not developed; there may be no obvious symptoms. When complications such as abdominal fluid buildup, bleeding varices or confusion develop, this is called decompensated cirrhosis. It needs closer follow-up and a revised plan. Symptoms alone cannot determine the stage.
- Pressure may rise in vessels carrying blood from the intestines to the liver, forming enlarged veins called varices, particularly in the esophagus and stomach. Reduced clearance of substances that affect the brain may cause confusion. Follow-up aims to detect and treat these problems early. Treating the cause can improve stability and reduce complications despite scarring. Cirrhosis does not mean an immediate transplant; specialist assessment determines timing if one is needed.
Can liver scarring improve?
- Fibrosis at stages F1–F3 can regress when its cause is treated, particularly at earlier stages. Improvement is not guaranteed, and F3 is advanced scarring that still needs careful follow-up.
- Cirrhosis (F4) can also improve in some people, but this does not necessarily restore a normal liver. Follow-up and any prescribed surveillance for liver cancer and varices remain important, even if blood tests or a stiffness measurement improve.
ILLUSTRATED PATIENT GUIDE
Fat, fibrosis and cirrhosis: what is the difference?
Fat in the liver does not automatically mean fibrosis or cirrhosis. Not everyone develops these stages.
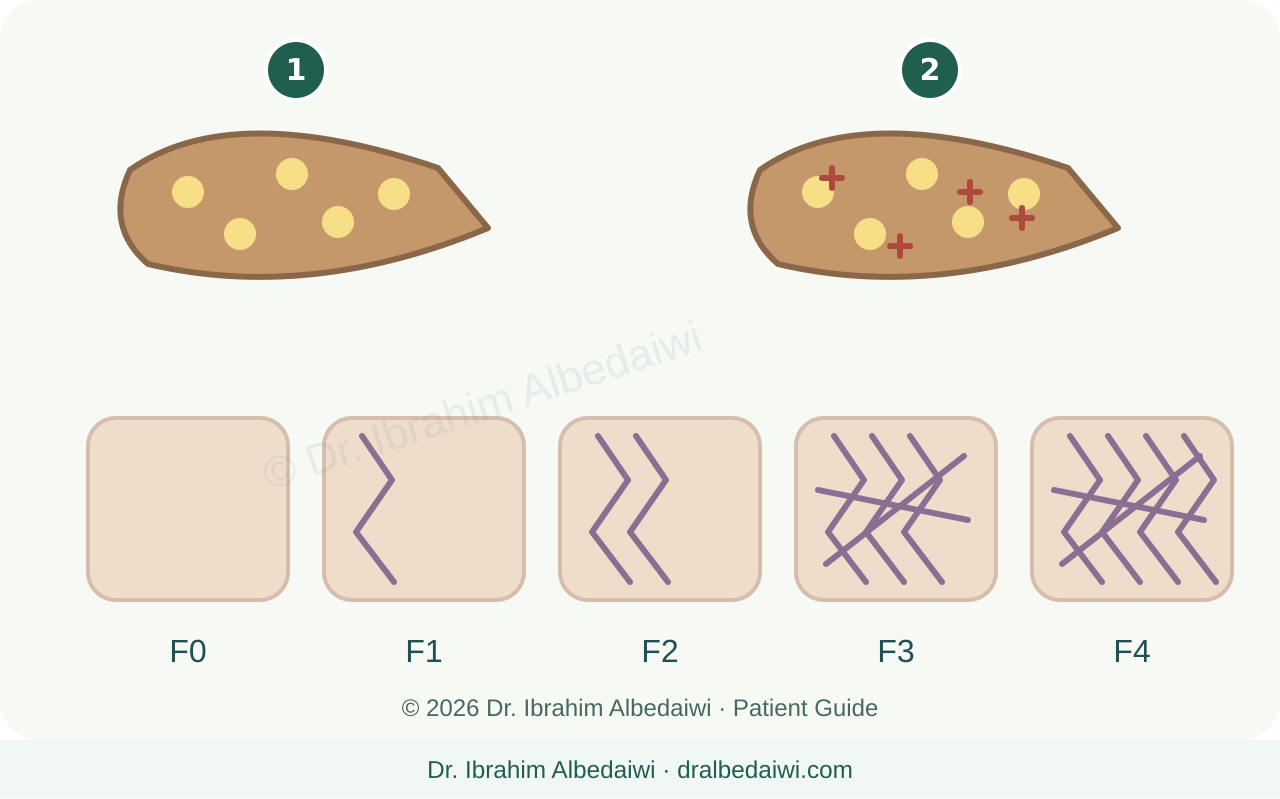
- 1 · Fat accumulation: MASLD
Fat builds up inside liver cells.
- 2 · Steatohepatitis: MASH
Fat accompanies liver-cell injury and inflammation; scars may develop.
- F0 · No fibrosis
This staging system describes scarring, not the amount of liver fat.
- F1–F3 · Fibrosis before cirrhosis
F1: mild · F2: moderate · F3: advanced bridging fibrosis, before F4.
- F4 · Cirrhosis
Extensive scarring alters liver structure and may affect blood flow and function.
Fibrosis can regress when its cause is treated, especially earlier stages. F4 can also improve, but this does not guarantee a normal liver or remove the need for follow-up. Progression is not inevitable; enzymes or stiffness alone cannot establish the stage.
© 2026 Dr. Ibrahim Albedaiwi · Original patient illustrationsFollow-up not to postpone
- Treat the cause, such as viral infection, autoimmune disease or metabolic problems. Many patients need liver imaging and an alpha-fetoprotein blood test every 6 months for early cancer detection.
- You may need medicine to lower pressure in the portal vein, the vein carrying blood to the liver, or an endoscopy to assess varices, according to your doctor’s plan. Bring your medicine list to every visit.
If you have abdominal fluid or swelling
- Your doctor may recommend limiting sodium to about 2 grams daily, equivalent to around 5 grams of salt from all sources. Reduce pickles, canned foods and very salty meals.
- Weigh yourself regularly as planned. Do not change diuretic doses or restrict fluids yourself; fluid restriction is not necessary for everyone.
Food to maintain muscle
- Eat small frequent meals with a bedtime snack, and include protein such as eggs, pasteurized yogurt, chicken or pulses as tolerated.
- Do not avoid protein because of confusion; the cause needs treatment alongside appropriate nutrition. Avoid prolonged fasting without discussing it with your doctor.
- Avoid raw seafood and meat and unpasteurized milk, and abstain from alcohol.
Medicines and confusion
- Avoid ibuprofen, diclofenac, sleeping medicines and herbs without approval. Even paracetamol requires an appropriate dose for your condition.
- If lactulose is prescribed, the usual aim is 2–3 soft stools daily according to your plan, not severe diarrhea. Do not stop it or raise the dose randomly.
- Ask family to watch for changes in sleep or concentration. Discuss vaccinations and transplant assessment if complications develop.
Kidneys and a low sodium result
- Kidney function can worsen with infection, dehydration, bleeding or medicines. Advanced liver disease can also disturb kidney blood flow, called hepatorenal syndrome. Tests are needed to distinguish these causes; do not assume every kidney problem is due to the liver. Markedly reduced urine needs urgent assessment.
- A low blood sodium result may reflect excess retained water, rather than too little salt in your food. Do not treat it by adding salt, drinking large amounts or stopping fluids. The team reviews fluid balance, medicines and blood tests before setting an individual plan.
Pain relief: check the ingredient and total dose
- When your clinician agrees it is suitable, paracetamol (acetaminophen) is often preferred to anti-inflammatory painkillers. In cirrhosis, the usual maximum is 2,000 mg in 24 hours from all products combined; your clinician may set a lower limit. Count cold remedies and combination painkillers too, and check the strength rather than counting tablets. Do not take ibuprofen or diclofenac tablets without specialist advice.
When to get help
Vomiting blood or black stools, new confusion or drowsiness, fever or abdominal pain with ascites, markedly reduced urine, or breathlessness.
Rapid weight gain or increasing abdominal size, worsening swelling, new jaundice or difficulty eating; contact the team early.
Guides for your care journey
Read the related guides together:
Related guides
Care after liver transplantation
Liver transplantation: when is evaluation needed?
Ascites: abdominal fluid and drainage
Hepatic encephalopathy: confusion and altered awareness
Portal hypertension and esophageal or gastric varices