

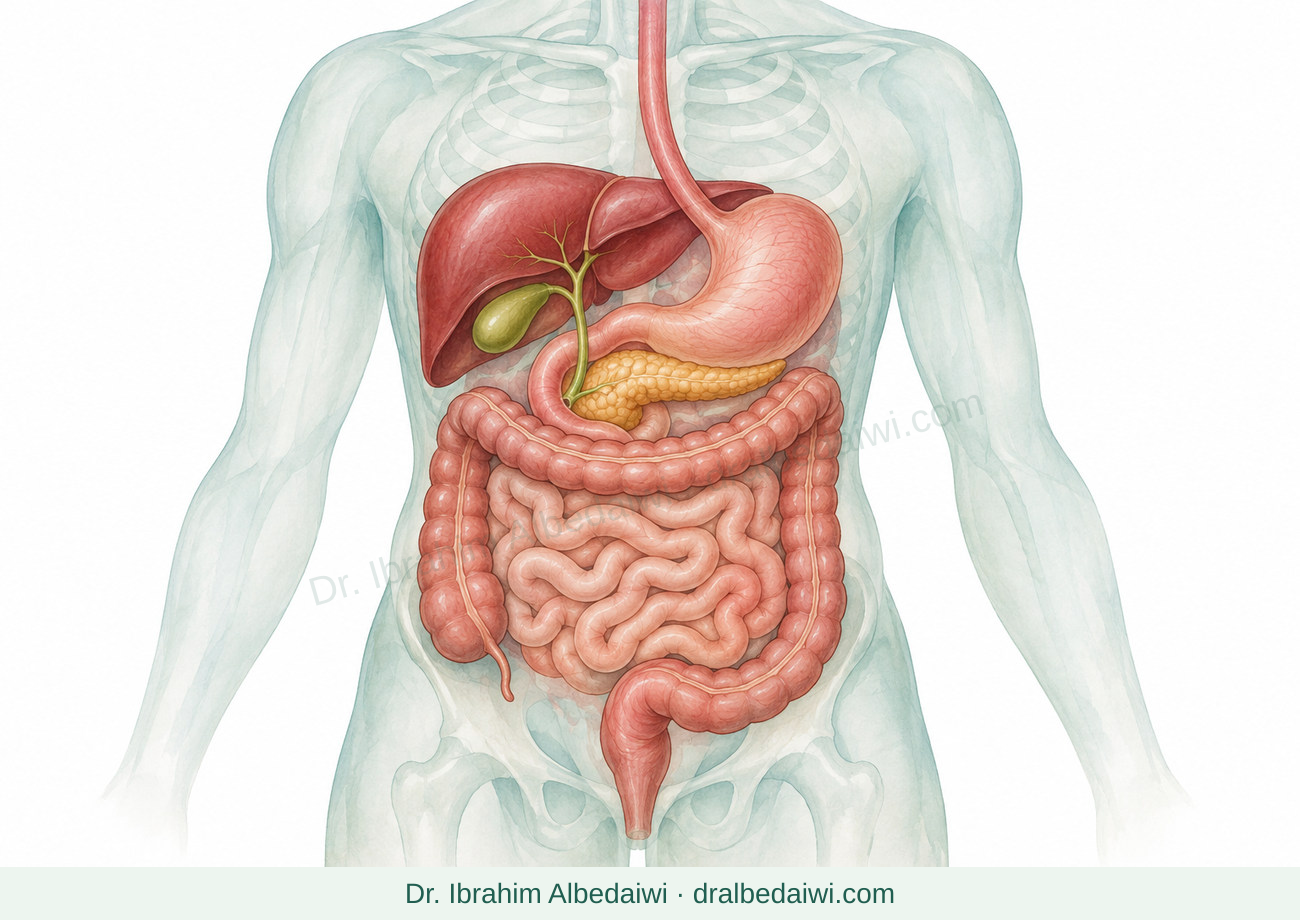

Bile and pancreatic duct endoscopy (ERCP)
Content date: 15 November 2026
ERCP mainly treats blocked or leaking ducts. If a stent is placed, its follow-up plan is an essential part of treatment.
Your next step
Confirm fasting, medicines and your escort; record the follow-up plan for any stent before leaving.
Get urgent help: Severe or increasing abdominal pain, especially with vomiting; fever or shaking chills; vomiting blood or black tarry stools; breathing difficulty or fainting. Seek emergency care and mention your recent ERCP or stent. Do not wait for follow-up.
What does ERCP do?
- Bile ducts carry fluid from the liver to the intestine; pancreatic ducts carry digestive juice. During ERCP, a scope passes through the mouth into the first part of the small intestine. Small instruments enter the duct opening, guided by contrast dye and X-rays. Sedation or anesthesia is used.
- Treatment may remove a stone, widen a narrowing, insert a drainage tube called a stent, or collect a sample. ERCP does not remove the gallbladder. When only diagnosis is needed, magnetic resonance imaging of the ducts (MRCP) or endoscopic ultrasound (EUS) may answer the question with less risk.
ILLUSTRATED PATIENT GUIDE
How does ERCP work?
ERCP is mainly used for treatment, such as removing a duct stone or placing a stent.
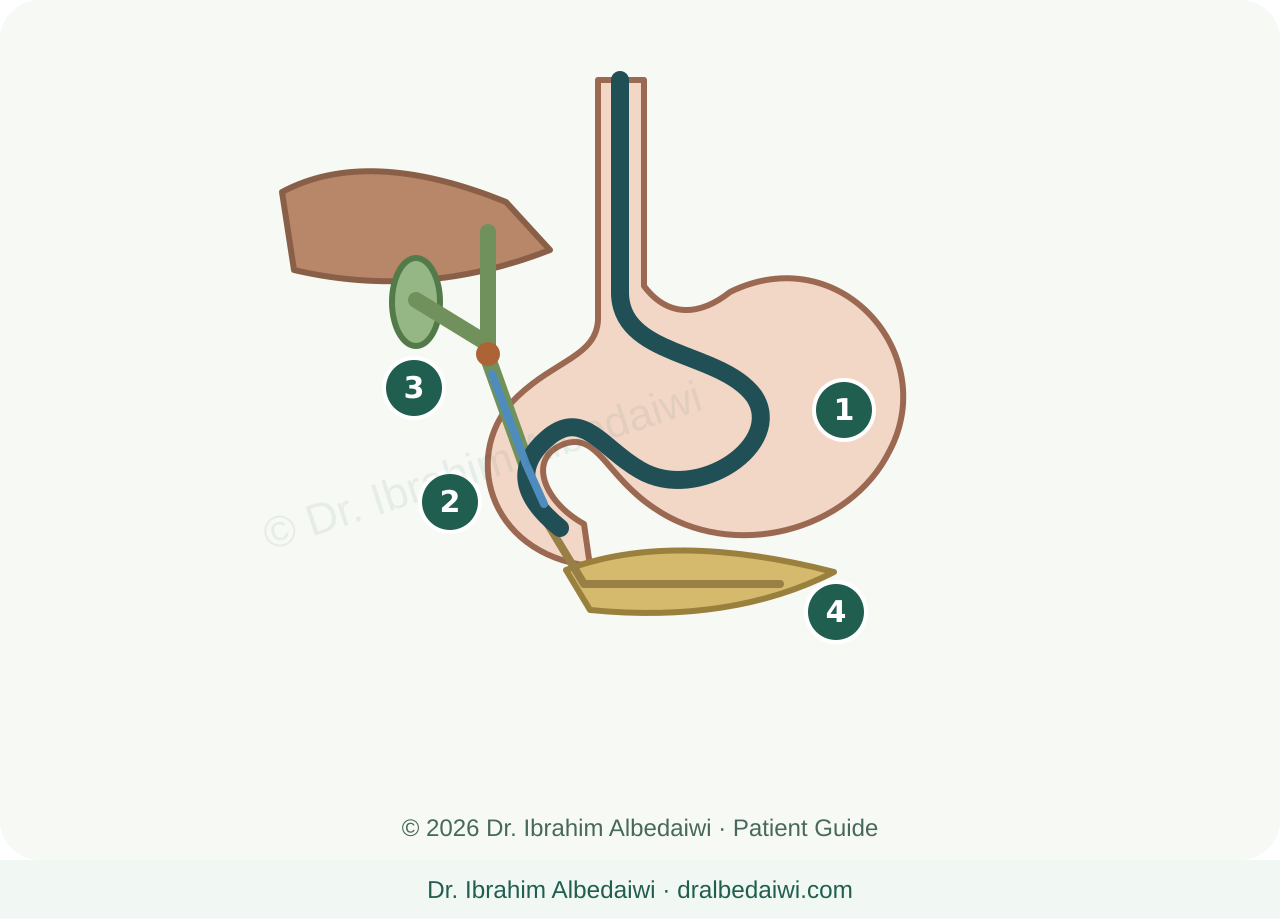
- 1 · Endoscope
Passes through the mouth and stomach into the duodenum.
- 2 · Duct opening
The scope tip stays in the duodenum beside the duct opening.
- 3 · Thin catheter
Enters the duct through its opening; the scope itself does not enter the duct. Contrast and X-rays show the duct.
- 4 · Pancreas
Its duct drains near the bile duct; treatment depends on the problem.
Simplified illustration. The team decides whether stone removal, narrowing treatment or a stent is needed.
© 2026 Dr. Ibrahim Albedaiwi · Original patient illustrationsBefore your appointment
- Send your medicine list, especially blood thinners and diabetes or weight-management medicines. Report allergies, possible pregnancy, heart, kidney or lung disease, and previous anesthesia or ERCP problems. Do not stop medicines yourself.
- Obtain written fasting and medicine instructions and arrange an adult escort. Bring imaging and surgery reports. Tell the unit if you have not followed the fasting instructions.
Risks and their prevention
- Risks include pancreatitis, bleeding, duct infection, perforation and sedation or anesthesia complications. Some require hospital treatment or another intervention. Ask about your individual benefits, risks and alternatives.
- To reduce pancreatitis risk, the team may give a rectal anti-inflammatory medicine if suitable, tailored intravenous fluids, and sometimes a temporary pancreatic duct stent. Heart or kidney problems affect these choices. These are clinician-directed measures; do not take extra painkillers yourself.
If treatment needs another session
- A large stone or difficult narrowing may require further specialist treatment. A temporary stent may allow drainage meanwhile. Occasionally another drainage method or surgery is needed. Less jaundice does not prove that the underlying problem is fully treated.
Leave with a written stent plan
- Ask where the stent is, its type and purpose, and when it must be removed or replaced. Many stents are temporary, but timing varies. Stents can block or move; feeling better is not a reason to miss follow-up.
- For a preventive pancreatic stent, ask how the team will check that it has passed or arrange removal if it remains. Contact the unit if no appointment arrives, and keep your procedure report.
After ERCP
- Brief bloating or a mild sore throat can occur. Observation or an overnight stay may be needed. Follow your specific instructions for food, fluids and restarting medicines.
- After sedation, avoid driving, machinery and important decisions for 24 hours, or longer if advised. Leave with an escort. Ask when sample results will arrive and whom to contact.
Stent follow-up record: before leaving the unit
Record these details with the endoscopy team in your report or personal notes, then tick what you have confirmed. These checkmarks are not sent to the team and do not book an appointment.
Fever or chills, new or severe abdominal pain, or worsening jaundice need urgent assessment. Do not wait for signs to occur together or for the stent appointment. Confusion, fainting or rapid deterioration require emergency care.
This record is a memory aid; it does not replace the unit’s follow-up system or appointments.
Open my personal treatment and follow-up plan
© 2026 Dr. Ibrahim Albedaiwi · dralbedaiwi.com
If a stent was placed

Read the illustration as text
Keep a follow-up plan after ERCP
- What was placed, and when?: Record the procedure date and stent details from your report.
- What happens next?: Does it need removal or exchange? Record the team’s planned date.
- Who arranges follow-up?: Keep the service’s official contact; call if no appointment arrives.
- When should I not wait?: Fever, severe pain or new jaundice needs urgent assessment.
Stent type determines the follow-up plan.
When to get help
Severe or increasing abdominal pain, especially with vomiting; fever or shaking chills; vomiting blood or black tarry stools; breathing difficulty or fainting. Seek emergency care and mention your recent ERCP or stent. Do not wait for follow-up.
No stent plan or sample result, or jaundice and itching that are not improving. Increasing jaundice needs urgent contact, especially with pain or fever.
Related guides
Bile duct stones and obstructive jaundice
Gallbladder and bile duct stones
Pancreatitis and pancreatic enzyme insufficiency